
November 3, 2020
Application of Platelet-Rich Plasma (PRP) in Medical Practice
The use of a patient's own blood to treat various diseases has been known since ancient times, practically since the origins of medicine. Today, platelet-rich plasma (PRP) is one of the approaches used in tissue engineering and cell therapy.
This article is our intellectual property. Access to this material is provided subject to voluntary payment of an author's fee equivalent to USD 10. We leave verification of payment to your conscience, following the European principle whereby people independently pay for the strawberries they pick in someone else's field.
Payments within Ukraine:
UA299358710000067321000114698 (Individual Entrepreneur Vitalii Verveiko)
Payments from other countries:
4149500019820029 (Vitalii Verveiko)
PAYPAL: cross-fm2@mail.ru
Biological Properties and Mechanism of Action of PRP
In clinical practice, it is generally accepted that the stimulatory effect of platelet-rich plasma may occur when its platelet concentration reaches at least 1,000,000/μL. When tissues are damaged, platelets play an important role in healing and regeneration through the release of growth factors.
Growth factors are natural polypeptides that exert a wide range of local biological effects on various cells. They participate in the key stages of regenerative processes, including chemotaxis, cell proliferation, cell migration and differentiation, tissue remodeling, and angiogenesis.
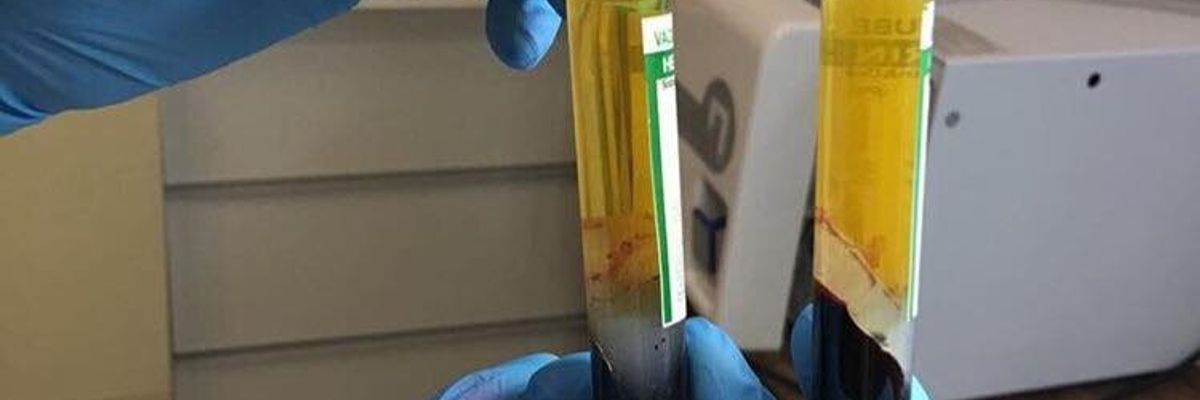
PRP contains the following growth factors:
- PDGF — platelet-derived growth factor;
- TGF-β — transforming growth factor beta;
- EGF — epidermal growth factor;
- VEGF — vascular endothelial growth factor.
In addition, plasma contains adhesion molecules — fibrin, fibronectin, and vitronectin — as well as cytokines.
Following centrifugation, the resulting plasma contains proteins, fibrinogen, nutrients (glucose and lipids), hormones, vitamins, enzymes, intermediate and final metabolic products, as well as inorganic ions involved in the cascade of tissue regeneration processes [12, 20].
Since PRP is derived from the patient's own blood, its use does not involve the risk of HIV or viral hepatitis transmission through donor material. It also reduces the likelihood of immune reactions associated with incompatibility of donor-derived components.
Classification of Platelet Concentrates
Various protocols are used to obtain PRP by centrifuging whole blood in one or two stages, with or without the addition of an anticoagulant. These methods produce different final products [12, 20].
One classification is based on the characteristics of the fibrin matrix and cellular composition, primarily leukocyte content. Four main groups are distinguished:
- P-PRP — pure platelet-rich plasma;
- L-PRP — leukocyte- and platelet-rich plasma;
- P-PRF — pure platelet-rich fibrin;
- L-PRF — leukocyte- and platelet-rich fibrin.
These groups differ in their preparation methods, mechanisms of action, and corresponding clinical applications [20].
Some researchers point out that many parameters used in PRP preparation, particularly centrifugation speed and duration, were historically selected empirically. This makes objective comparisons between the results of different protocols difficult [20].
Some authors [17] identified a correlation between platelet concentration in PRP and the initial platelet count in the donor's whole blood. However, no statistically significant correlation between these parameters was established. A statistically significant but clinically insignificant influence of the subjects' sex on platelet concentration was identified. No effect of age was detected.
The Importance of PRP Cellular Composition
The possible influence of cellular composition on clinical outcomes has been a subject of debate in the use of PRP.
Some authors argue that the presence of leukocytes in injectable PRP may negatively affect clinical outcomes because of the risk of stimulating an inflammatory response [31]. Other researchers disagree, pointing to the ability of leukocytes to produce analgesic mediators and participate in the regulation of healing through their natural anti-inflammatory properties [31, 33].
Therefore, when assessing the quality of a platelet concentrate, it is important to consider not only the platelet count but also the cellular composition of the final product.
Applications of PRP in Dentistry and Maxillofacial Surgery
PRP has become particularly widespread in dental implantology [2]. According to some authors, its use in bone grafting and the prevention of jaw atrophy before dental implant placement contributed to earlier bone formation [4]. PRP combined with autologous bone tissue and various bone substitute materials has also been proposed for maxillary alveolar ridge augmentation [21, 29, 30].
One of the main mechanisms of regeneration is improved tissue blood supply through the stimulation of angiogenesis. When platelets are activated and degranulate, they release growth factors involved in regulating tissue repair. These polypeptide growth factors are present in PRP in biologically determined proportions.
In maxillofacial reconstructive surgery, platelet-rich autologous plasma gel and L-PRF membranes are used. Their application has also been described in children with congenital cleft lip and palate [18, 24].
Platelet-rich plasma is also widely used in periodontology [18]. An injectable method for locally stimulating regenerative processes using PRP obtained by centrifugation in Plasmolifting™ tubes has been described. The study reported a reduction in inflammation, a decrease in inflammatory cell infiltrates, and fewer inflammatory cells in affected gingival tissues [11].
Applications of PRP in Cardiovascular Surgery
Numerous studies investigating the effectiveness of PRP in cardiovascular surgery indicate its potential benefits for patients following cardiac surgery.
Reinfusion of autologous platelet-rich plasma may improve hemostasis following cardiopulmonary bypass, help reduce blood loss, decrease the need for donor blood transfusions, and contribute to the correction of several hematological abnormalities [16, 19, 21].
Applications of PRP in Reconstructive and Abdominal Surgery
A clinical case of severe fibrous dysplasia affecting the fronto-orbital region has been described, in which reconstruction was performed using PRP [26]. The authors reported long-term remission of symptoms and earlier bone formation. Combining PRP with allotransplantation or transplantation of fragmented bone tissue was considered a safe and relatively simple treatment approach.
Clinical studies in abdominal surgery confirmed the effectiveness of high-fibrin-content fibrin glue in Lichtenstein hernioplasty in patients with coagulopathies associated with liver disease, as well as in patients receiving long-term anticoagulant therapy. The use of fibrin sealants may improve surgical outcomes, accelerate hemostasis, and reduce blood loss and complications [5].
An experimental histological study of aseptic soft-tissue wound healing using PRP demonstrated stimulation of collagen formation, epithelialization, and vascularization, as well as faster scar tissue formation [10].
Applications of PRP in Orthopedics and Traumatology
PRP is used in both surgical and conservative treatment of inflammatory joint diseases [23, 27].
In an experimental rat model of knee osteoarthritis, intra-articular administration of platelet gel was investigated [23]. At the same time, the effectiveness of PRP in treating musculoskeletal soft-tissue injuries — partial tears of ligaments, muscles and tendons, as well as tendinopathies — as either an independent treatment or an adjunctive method following surgery remains a subject of discussion.
According to L. Yu. Shirokova et al. (2012), local application of PRP in patients with gonarthrosis and early manifestations of osteoarthritis was associated with a significant improvement in knee joint function. In typical radiographically confirmed stage II–III gonarthrosis, the positive effect of PRP was short-lived and was observed mainly during the first month. In severe gonarthrosis complicated by synovitis, treatment proved ineffective.
In an experimental rabbit model of articular surface defects, intra-articular PRP administration stimulated hyaline cartilage regeneration and improved its qualitative and quantitative characteristics [14].
Applications of PRP in Plastic Surgery and Otorhinolaryngology
The use of PRP-derived products in aesthetic and plastic surgery is of particular interest [25].
In otorhinolaryngology, PRP has been used to stimulate tympanic membrane regeneration in cases of small defects and following tympanoplasty [13]. According to certain studies, using PRP to seal the space around a prosthesis during piston stapedoplasty reduced the risk of sensorineural hearing loss compared with using adipose tissue or leaving the prosthesis unsupported. A reduction in the likelihood and intensity of tinnitus following surgery was also reported [7].
In patients with chronic suppurative otitis media, the use of PRP during simultaneous sanitation surgery and tympanoplasty, as a support for the neotympanic graft, was associated with faster postoperative cavity healing and hearing restoration [3]. A reduced risk of perforations, atrophic changes in the tympanic membrane, and adhesions within the reconstructed tympanic cavity was also reported [9].
In an experimental study involving six pigs, filling the tympanic cavity with PRP preserved the ventilation function of the Eustachian tube. The clot was completely eliminated from the tympanic cavity without scar tissue or adhesions forming [8].
Frontal sinus obliteration using a tibial bone graft and PRP administration following sinus irrigation and curettage may be an effective treatment for chronic frontal sinus osteomyelitis [22].
In the treatment of epistaxis, fibrin glue demonstrated greater effectiveness than nasal packing with a hemostatic sponge, chemical cauterization, and diathermic coagulation [32].
However, no beneficial effect of PRP was identified following endonasal endoscopic surgical procedures, and the study was terminated prematurely [28].
In a study involving 257 patients undergoing rhinoplasty and septoplasty, protein-platelet clots prepared from PRP demonstrated significant advantages over other dressing materials [1].
According to published data, local application of PRP following tonsillectomy reduced the likelihood of postoperative bleeding, decreased the intensity of throat pain and bacterial colonization of the wound surface, and accelerated tissue regeneration [15].
Conclusions
Platelet-rich plasma is a biotechnology product that has become widely used in clinical practice. Its safety and effectiveness are being investigated across numerous medical fields; however, a considerable number of unresolved issues remain.
Based on an analysis of scientific publications, several important areas for further research can be identified:
- Accurate characterization of the cellular composition of the final product is essential, particularly the platelet count and the presence and concentration of leukocytes and other cellular components.
- It should be taken into account that the cellular composition of PRP may influence the inflammatory response and tissue regeneration processes.
- Standardization of PRP preparation protocols would facilitate the selection of appropriate methods and improve the reproducibility of results in everyday clinical practice.
- Objective assessment of effectiveness requires consideration not only of platelet concentration but also of the preparation technology, cellular composition, and characteristics of the final product.
Scientific References
[1] Krainik I. V., Balin V. M., Mikhailov V. V. et al. Protein-platelet dressings in reconstructive nasal surgery // Annals of Plastic, Reconstructive and Aesthetic Surgery. 2012; No. 3: 29–42.
[2] Bulanikov A. S., Semenov V. P. Improving the effectiveness of bone grafting using platelet-rich plasma to fill human bone defects // Medical Care. 2007; No. 1: 22–25.
[3] Zavyalov F. N., Goncharova O. G. Results of using autologous platelet-rich plasma in patients following middle ear surgery // Bulletin of Otorhinolaryngology. 2011; No. 1: 28–30.
[4] Ivanov P. Yu., Zhuravlev V. P., Makeev O. G. Application of platelet-rich plasma for the prevention of jaw atrophy prior to dental implantation // Bulletin of the Medical Academy of Sciences. 2011; No. 1: 76–78.
[5] Popov P. A., Popov Yu. P., Magomedova L. A. et al. Treatment of complications following abdominal surgery using platelet-rich plasma // Surgeon. 2014; No. 6: 4–11.
[6] Shirokova L. Yu., Noskov S. M., Bakhtiarova T. I. et al. Local treatment of gonarthrosis using autologous platelet-rich plasma // STM. 2012; No. 1: 97–100.
[7] Semenov F. V., Banashek-Meshcheryakova T. V. Application of platelet-rich plasma for the prevention of cochleovestibular disorders during piston stapedoplasty // Bulletin of Otorhinolaryngology. 2011; No. 3: 47–50.
[8] Semenov F. V., Banashek-Meshcheryakova T. V., Semenov V. F. Morphological and functional changes in the tympanic cavity following its filling with platelet-rich plasma: an experimental study // Bulletin of Otorhinolaryngology. 2011; No. 4: 43–45.
[9] Semenov F. V. Otoscopic and endoscopic evaluation of long-term outcomes of tympanoplasty performed using platelet-rich plasma // Bulletin of Otorhinolaryngology. 2013; No. 3(64): 132–135.
[10] Glukhov A. A., Ostroushko A. P., Semenov S. N. et al. Structural and functional features of aseptic soft-tissue wound healing using platelet-rich plasma // Bulletin of Experimental and Clinical Surgery. 2010; Vol. 3, No. 3: 210–213.
[11] Akhmerov R. R., Ovechkina M. V., Tsiplakov D. E. et al. Plasmolifting™ technology: an injectable form of platelet autologous plasma for the treatment of chronic periodontitis of mild to moderate severity // Periodontology. 2013; No. 1: 45–52.
[12] Tolstov D. A., Bogdan V. G. Platelet concentrates: classification, preparation technologies, and biological effects. 2012: 141–144.
[13] Toropova L. A., Andriyanova I. V., Zhuikova T. V. Possibilities of restoring tympanic membrane elasticity and integrity using platelet-rich plasma // Proceedings of the Conference of Otorhinolaryngologists and Audiologists. 2013: 34.
[14] Mostikov O. M., Deikalo V. P., Samsonova I. V. et al. Effectiveness of platelet-rich plasma in the treatment of traumatic defects of articular cartilage // Surgery News. 2013; Vol. 21, No. 4: 3–9.
[15] Yakobashvili I. Yu., Semenov F. V. Effect of local application of platelet-rich plasma on wound healing following tonsillectomy // Bulletin of Otorhinolaryngology. 2008; No. 4: 26–30.
[16] Yamamoto K., Hayashi J., Miyamura H. et al. A comparative study of the effect of autologous platelet-rich plasma and fresh autologous whole blood on haemostasis after cardiac surgery // Cardiovascular Surgery. 1996; 4(1): 9–14.
[17] Weibrich G., Kleis W. K., Hitzler W. E. et al. Comparison of the platelet concentrate collection system with the plasma-rich-in-growth-factors kit to produce platelet-rich plasma: a technical report // International Journal of Oral and Maxillofacial Implants. 2005; 20(1): 118–123.
[18] Simonpieri A., Del Corso M., Vervelle A. et al. Current Knowledge and Perspectives for the Use of Platelet-Rich Plasma (PRP) and Platelet-Rich Fibrin (PRF) in Oral and Maxillofacial Surgery. Part 2: Bone Graft, Implant and Reconstructive Surgery // Current Pharmaceutical Biotechnology. 2012; 13: 1231–1256.
[19] Giordano G. F., Giordano G. F. Jr., Rivers S. L. et al. Determinants of Homologous Blood Usage Utilizing Autologous Platelet-Rich Plasma in Cardiac Operations // Annals of Thoracic Surgery. 1989; 47: 897–902.
[20] Dohan Ehrenfest D. M., Rasmusson L., Albrektsson T. Classification of platelet concentrates: from pure platelet-rich plasma (P-PRP) to leucocyte- and platelet-rich fibrin (L-PRF) // Trends in Biotechnology. 2009; 27: 158–167.
[21] Kashima I., Ueda T., Shimizu H. et al. Efficacy of autologous platelet-rich plasma in thoracic aortic aneurysm surgery // Japanese Journal of Thoracic and Cardiovascular Surgery. 2000; 48(11): 708–712.
[22] Acosta-Feria M., Infante-Cossio P., Hernandez-Guisado J. M. et al. Frontal sinus obliteration using tibial bone graft and platelet-rich plasma for the treatment of chronic osteomyelitis // Neurocirugia. 2006; 17(4): 351–356.
[23] Guner S., Buyukbebeci O. Analyzing the Effects of Platelet Gel on Knee Osteoarthritis in the Rat Model // Clinical and Applied Thrombosis/Hemostasis. 2013; 19(5): 494–498.
[24] Horowitz B., Busch M. Estimating the pathogen safety of manufactured human plasma products: application to fibrin sealants and to thrombin // Transfusion. 2008; 48: 1739–1753.
[25] Man D., Plosker H., Winland-Brown J. E. The use of autologous platelet-rich plasma (platelet gel) and autologous platelet-poor plasma (fibrin glue) in cosmetic surgery // Plastic and Reconstructive Surgery. 2001; 107(1): 229–237.
[26] Mendonca-Caridad J. J., Juiz-Lopez P., Rubio-Rodriguez J. P. Frontal sinus obliteration and craniofacial reconstruction with platelet-rich plasma in a patient with fibrous dysplasia // International Journal of Oral and Maxillofacial Surgery. 2006; 35(1): 88–91.
[27] Mishra A., Pavelko T. Treatment of chronic elbow tendinosis with buffered platelet-rich plasma // American Journal of Sports Medicine. 2006; 34(11): 1774–1778.
[28] Rice D. H. Platelet-rich plasma in endoscopic sinus surgery // Ear, Nose and Throat Journal. 2006; 85(8): 516–518.
[29] Rosenberg E. S., Torosian J. Sinus grafting using platelet-rich plasma — initial case presentation // Practical Periodontics and Aesthetic Dentistry. 2000; 12(9): 843–850.
[30] Sonnleitner D., Huemer P., Sullivan D. Y. A simplified technique for producing platelet-rich plasma and platelet concentrate for intraoral bone grafting techniques: a technical note // International Journal of Oral and Maxillofacial Implants. 2000; 15(6): 879–882.
[31] Bielecki T., Dohan Ehrenfest D. M., Everts P. A. et al. The role of leukocytes from L-PRP/L-PRF in wound healing and immune defense: new perspectives // Current Pharmaceutical Biotechnology. 2012; 13: 1153–1162.
[32] Vaiman M., Segal S., Eviatar E. Fibrin glue treatment for epistaxis // Rhinology. 2002; 40(2): 88–91.
[33] Everts P. A., van Zundert A., Schönberger J. P. A. M. et al. What do we use: platelet-rich plasma or platelet-leukocyte gel? // Journal of Biomedical Materials Research. 2008; 85: 1135–1136.
Full or partial reproduction, copying, or modification of this article without the copyright holder's permission is prohibited!


